Skip to content
BuyandBill.com — Physician Administered Drug Pricing
  • Search
    • Search
    • HCPCS Code Lookup
    • NDC Lookup
    • Drug Price Lookup
  • Drug Codes
    • All Drug Codes
    • A Code
    • C Code
    • J Code
    • P Code
    • Q Code
    • S Code
    • CPT Vaccine Code
    • NOC Code
    • Administration Code
  • Coding References

    • CPT Administration Codes
    • HCPCS Modifiers
    • HCPCS Approvals
    • Medically Unlikely Edits
    • Place of Service Codes
    • NDC Listing Errors
    • SAD Exclusion List
    • Wastage Guidance

    Learn

    • Blog
    • Newsletter
    • Bobbi Buell's Newsletter
    • Glossary
    • Buy-and-Bill Basics
    • Biosimilars
    • 505(b)(2) Drugs
    • Drug Shortages

    Tools

    • Billing Calculator
    • Drug Comparative Graphing
    • Biosimilar Analysis
    • Part B Reimbursement

    Solutions

    • Drug Sponsorship
    • Drug Market Research
  • Subscription Options
    • Contact Us
    • Schedule Consultation
Login
  • Login
  • Register

Drug Alerts and Special Reports

Key reimbursement alerts for office-administered drugs — C-Code, J-Code, NDC, and NCCN alerts plus pricing updates, sent on behalf of pharma manufacturers.

Subscribe To Newsletter

FDA Approved 01/03/2024

Sponsored Message: New FDA Approval in Locally Advanced/Metastatic Urothelial Cancer (mUC) - 1/3/24

Recent FDA Indication Approval in Locally Advanced/Metastatic Urothelial Cancer (mUC) Full Prescribing Information including BOXED WARNING NOW APPROVED! Now Approved in Combination With Pembrolizumab as a First-Line Treatment for Locally Advanced/ Metastatic Urothelial Cancer (mUC) Regardless of Cisplatin Eligibility Astellas Pharma Inc. and Seagen are pleased to announce the U.S. Food and Drug Administration (FDA) approval of PADCEV + pembrolizumab for the treatment of adult patients with locally advanced or metastatic urothelial cancer (mUC) based on data from the EV-302 trial. This latest approval expands the indication of PADCEV + pembrolizumab and the patient population that may benefit from this treatment. Indication PADCEV ® , in combination with pembrolizumab, is indicated for the treatment of adult patients with locally advanced or metastatic urothelial cancer (mUC). PADCEV, as a single agent, is indicated for the treatment of adult patients with locally advanced or mUC who…
Read More
J-Code 12/20/2023

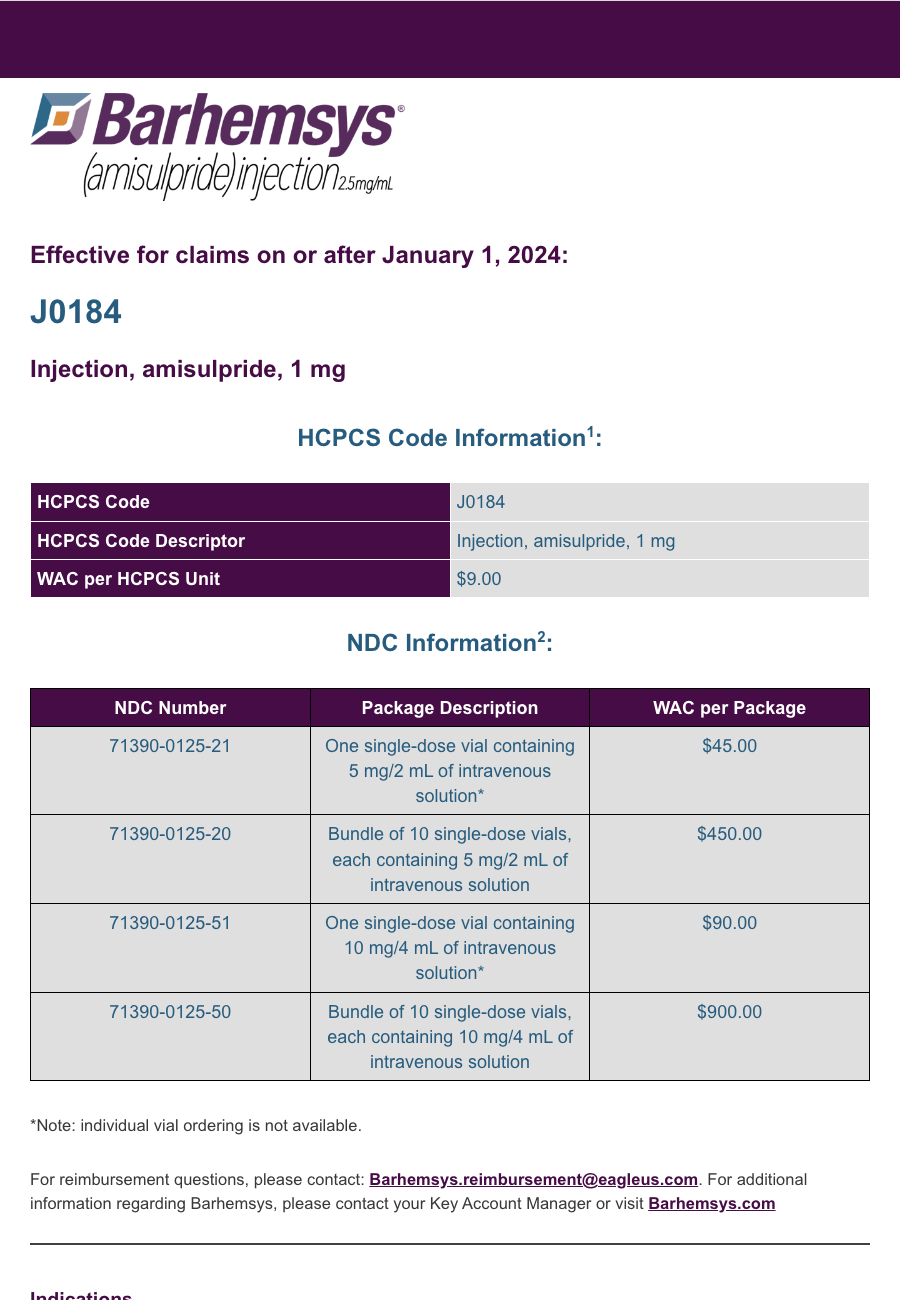
Permanent J-Code for BARHEMSYS® (amisulpride injection): Available January 1, 2024 - 12/20/2

Effective for claims on or after January 1, 2024: J0184 Injection, amisulpride, 1 mg HCPCS Code Information 1 : HCPCS Code J0184 HCPCS Code Descriptor Injection, amisulpride, 1 mg WAC per HCPCS Unit $9.00 NDC Information 2 : NDC Number Package Description WAC per Package 71390-0125-21 One single-dose vial containing 5 mg/2 mL of intravenous solution* $45.00 71390-0125-20 Bundle of 10 single-dose vials, each containing 5 mg/2 mL of intravenous solution $450.00 71390-0125-51 One single-dose vial containing 10 mg/4 mL of intravenous solution* $90.00 71390-0125-50 Bundle of 10 single-dose vials, each containing 10 mg/4 mL of intravenous solution $900.00 *Note: individual vial ordering is not available. For reimbursement questions, please contact: [email protected] . For additional information regarding Barhemsys, please contact your Key Account Manager or visit Barhemsys.com Indications Barhemsys is a selective dopamine-2 (D 2 ) and dopamine-3 (D 3 ) receptor antagonist…

Read More
C-Code 12/13/2023

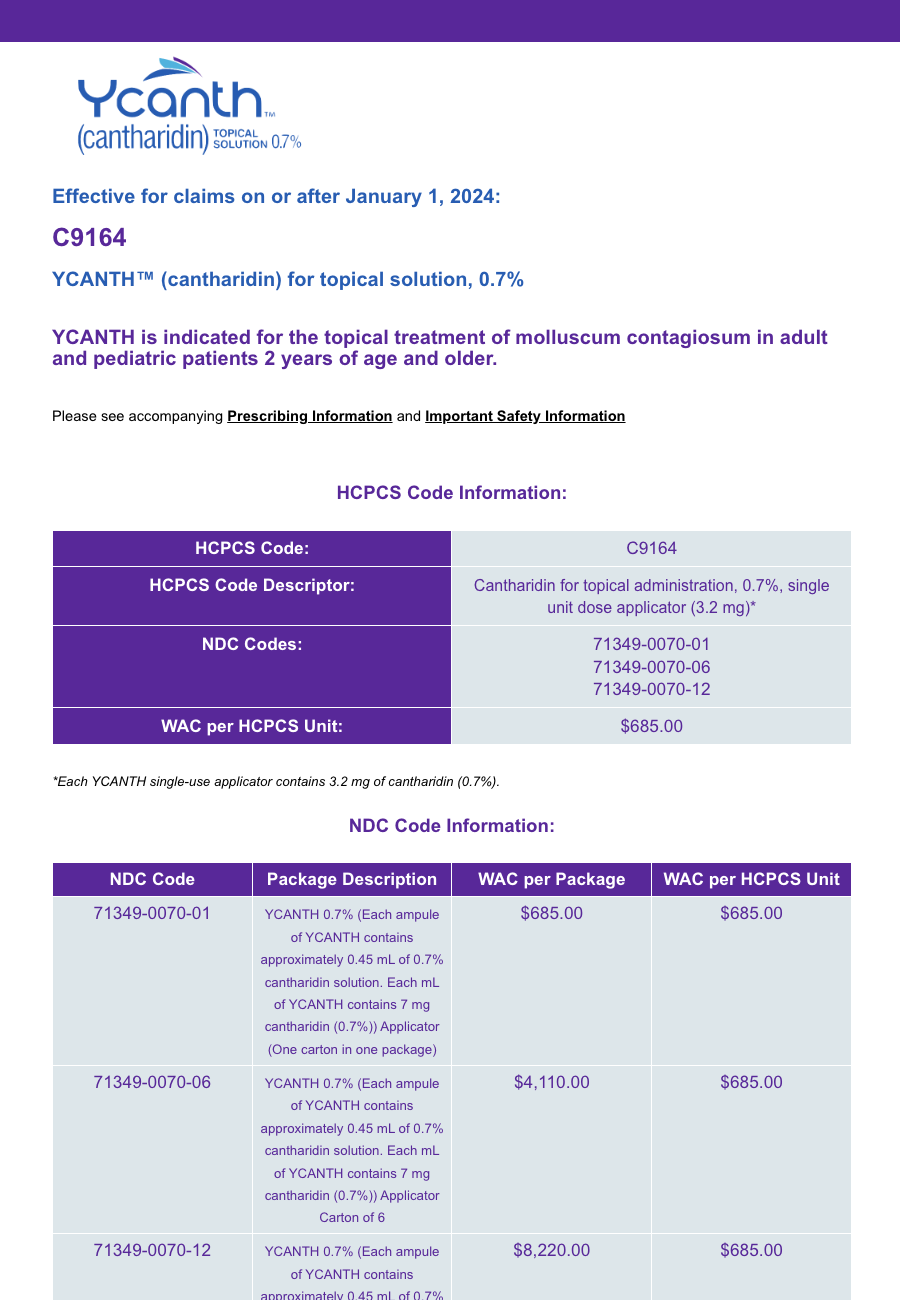
Temporary C-Code for YCANTH® (cantharidin): C9164 - 12/13/23

Available January 1, 2024 Effective for claims on or after January 1, 2024: C9164 YCANTH™ (cantharidin) for topical solution, 0.7% YCANTH is indicated for the topical treatment of molluscum contagiosum in adult and pediatric patients 2 years of age and older. Please see accompanying Prescribing Information and Important Safety Information HCPCS Code Information: HCPCS Code: C9164 HCPCS Code Descriptor: Cantharidin for topical administration, 0.7%, single unit dose applicator (3.2 mg)* NDC Codes: 71349-0070-01 71349-0070-06 71349-0070-12 WAC per HCPCS Unit: $685.00 *Each YCANTH single-use applicator contains 3.2 mg of cantharidin (0.7%). NDC Code Information: NDC Code Package Description WAC per Package WAC per HCPCS Unit 71349-0070-01 YCANTH 0.7% (Each ampule of YCANTH contains approximately 0.45 mL of 0.7% cantharidin solution. Each mL of YCANTH contains 7 mg cantharidin (0.7%)) Applicator (One carton in one package) $685.00 $685.00 71349-0070-06 YCANTH 0.7% (Each ampule of YCANTH…

Read More
Pricing 12/13/2023

Announcing a Price Change for Paragard® (intrauterine copper contraceptive) - 12/12/23

Paragard Customer, Effective January 1, 2024, the pricing of Paragard will change as outlined below. Please take a moment to update any of your reimbursement, billing, and ordering systems to reflect this change. PARAGARD Pricing and Coding Information: HCPCS Code Labeler 11 Digit NDC Price Effective Date Product Description WAC Estimated AWP J7300 COOPERSURGICAL 59365-5128-01 1/1/24 PARAGARD T380A 10 YEARS $1085 $1302 CooperSurgical is notifying all customers and business associates about this change, and we would appreciate your partnership in helping us ensure that all systems and locations involved with Paragard are updated with the new Paragard pricing. For any questions, contact CooperSurgical at 1.877.PARAGARD. Paragard is a registered trademark of CooperSurgical, Inc. © 2023 CooperSurgical, Inc. C-US-PAR-000444 December 2023.

Read More
12/05/2023

XACIATO™ for the treatment of Bacterial vaginosis - 12/5/23

Learn more about XACIATO Bacterial vaginosis (BV) can be embarrassing for patients. XACIATO TM (clindamycin phosphate) vaginal gel 2%, a single-dose treatment for BV in females 12 years of age and older, is available in pharmacies. BV affects as many as 21 million women in the United States. Many current treatments need to be used for multiple days. XACIATO treats BV in a single dose . • A single intravaginal dose at any time of day. • Thermosetting formulation for gradual release of clindamycin. 1 - XACIATO vaginal gel increases viscosity at body temperature and gradually releases clindamycin over time. a • Robust efficacy in both new and recurrent BV: - Significantly higher clinical cure at day 21-30 vs placebo in both subsets of patients with ≤3 episodes or >3 episodes (recurrent) of BV in the past 12 months. 2 Treatment difference: ≤3 episodes of BV in the past 12 months: 32.2%; 95% CI: 13.9, 50.4; P =0.001 (XACIATO: N=101, placebo: N=46). Recurrent BV: 46.9%; 95% CI: 10.1…

Read More
J-Code 11/30/2023

Permanent J-Code for RYSTIGGO® (rozanolixizumab-noli): Available January 1, 2024 - 11/30/23

Corrected WAC Pricing Effective for claims on or after January 1, 2024 1 : J9333 Injection, rozanolixizumab-noli, 1 mg RYSTIGGO (rozanolixizumab-noli) is the first and only FDA-approved targeted treatment for both anti-acetylcholine receptor (AChR) and anti-muscle-specific tyrosine kinase (MuSK) antibody-positive (Ab+) adult patients with generalized myasthenia gravis (gMG). 2 *Corrected WAC Pricing* HCPCS Code 1 J9333 HCPCS Code Descriptor 1 Injection, rozanolixizumab-noli, 1 mg NDC Codes 2 50474-980-79 50474-0980-79* Package Description 2 Each carton of RYSTIGGO contains one single-dose glass vial containing 280 mg/2 mL (140 mg/mL) WAC per HCPCS Unit 3 $21.61 WAC per Package 3 $6,050 ICD-10-CM Codes 4,† G70.00 Myasthenia gravis without (acute) exacerbation G70.01 Myasthenia gravis with (acute) exacerbation *For certain purposes, including the proper billing of drug products, an 11-digit NDC may be required. † These diagnosis codes are informational and not intended to be directive…

Read More
FDA Approved 11/14/2023

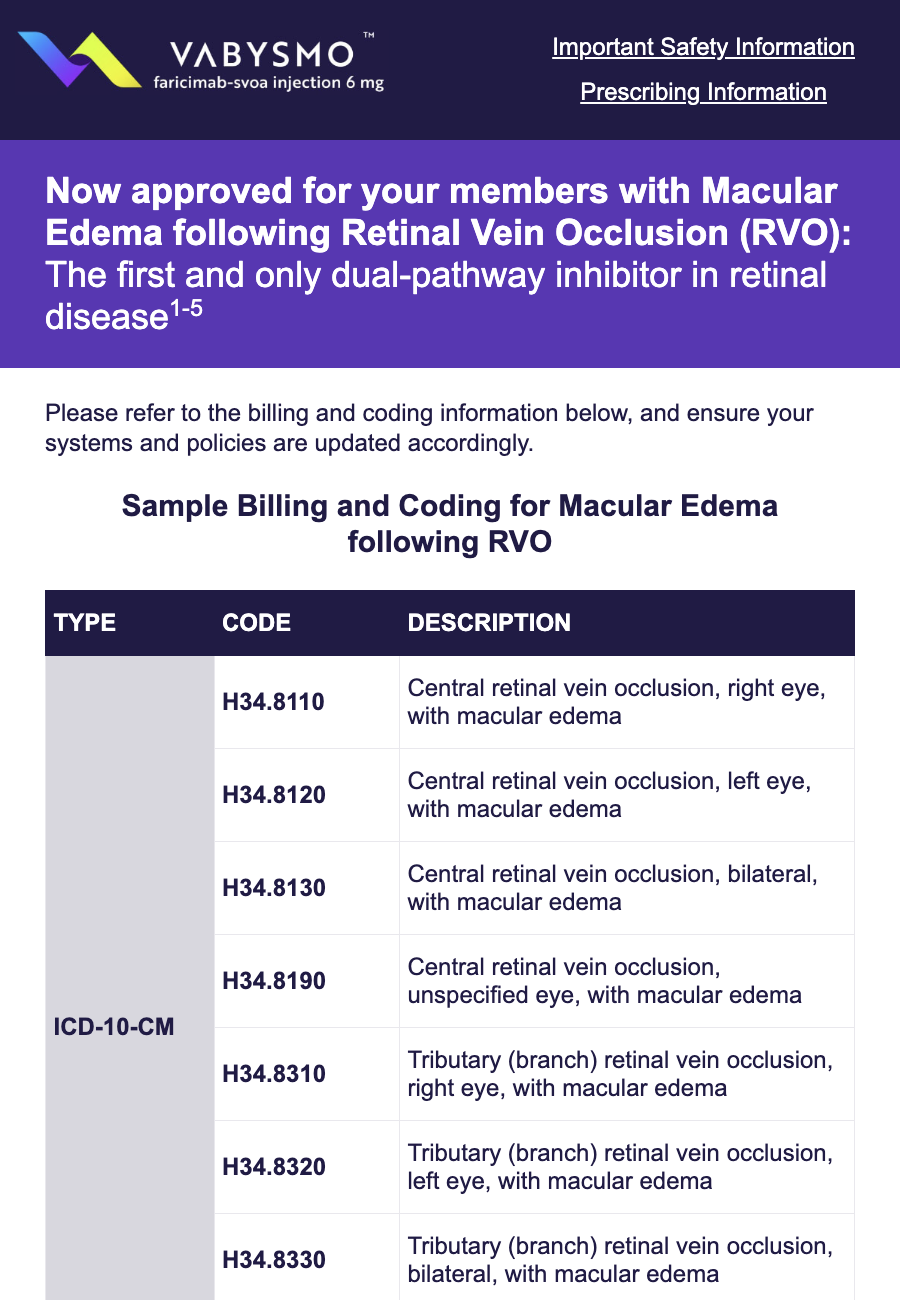
VABYSMO® (faricimab-svoa): New Indication Now Approved - 11/6/23

View in browser Important Safety Information Prescribing Information Now approved for your members with Macular Edema following Retinal Vein Occlusion (RVO): The first and only dual-pathway inhibitor in retinal disease 1-5 Please refer to the billing and coding information below, and ensure your systems and policies are updated accordingly. Sample Billing and Coding for Macular Edema following RVO TYPE CODE DESCRIPTION ICD-10-CM H34.8110 Central retinal vein occlusion, right eye, with macular edema H34.8120 Central retinal vein occlusion, left eye, with macular edema H34.8130 Central retinal vein occlusion, bilateral, with macular edema H34.8190 Central retinal vein occlusion, unspecified eye, with macular edema H34.8310 Tributary (branch) retinal vein occlusion, right eye, with macular edema H34.8320 Tributary (branch) retinal vein occlusion, left eye, with macular edema H34.8330 Tributary (branch) retinal vein occlusion, bilateral, with macular edema H34.8390 Tributary (branch)…

Read More
Biosimilar 10/10/2023

Samsung Bioepis Biosimilar Market Report 3rd Edition, Q4 2023 - 10/10/23

SAMSUNG BIOEPIS Biosimilar Market Report 3 rd Edition, Q4 2023 Download Here I. US Biosimilars Approval and Launch Status II. Biosimilar Price - Medical Benefit Oncology Supportive Care Immunology & Ophthalmology - Pharmacy Benefit Immunology and Endocrinology III. Biosimilar Market Dynamics - Biosimilar Market Adoption & Price Erosion - Market Share & Price Trends Oncology Supportive Care Immunology Endocrinology Ophthalmology IV. Biosimilars Deep Dive Download Here © 2023 Samsung Bioepis Co., Ltd. All Rights Reserved. 9/2023. BuyandBill.com SAMSUNG…

Read More
10/05/2023

Setmelanotide as a Protein replacement agent: USP Medicare Modeling Guidelines - 10/5/23

On September 29th, The United States Pharmacopeia (USP) issued the Medicare Modeling Guidelines (MMG) version 9.0 including setmelanotide as a Protein replacement agent Read the USP 9.0 Guidelines Updates to USP Medicare Modelling Guidelines include changes in therapeutic uses of covered Part D drugs and the additions of new covered Part D drugs. Anti-obesity agents are not included in the USP-MMG guidelines. The USP Medicare Model Guidelines (MMG) is an independent drug classification system designed for Centers for Medicare & Medicaid Services (CMS) Part D formulary submissions Being recognized as a “Genetic or Enzyme or Protein Disorder: Replacement, Modifiers, Treatment” means that setmelanotide is not categorized as an anti-obesity agent by USP The members of the USP Council of Experts, the Healthcare Safety and Quality Expert Committee (HSQ EC) comprised of independent pharmacologists, clinical pharmacists, academicians, formulary specialists, providers, beneficiaries, drug…

Read More
FDA Approved 10/04/2023

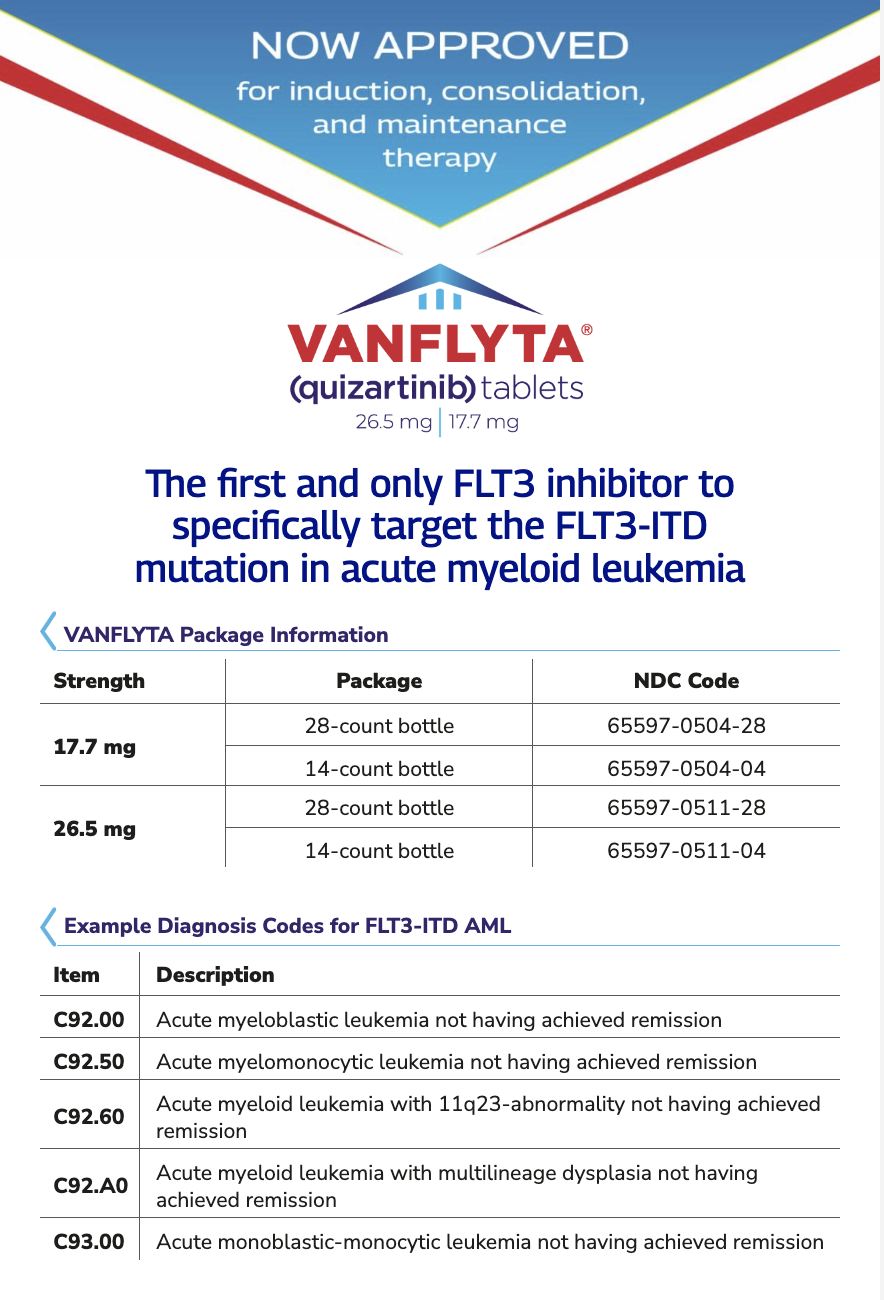
Now Approved: VANFLYTA® (quizartinib) for FLT3-ITD AML - 10/3/23

Learn more about this new treatment option. Review the PI and Boxed WARNINGS. ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ ‌ The first and only FLT3 inhibitor to specifically target the FLT3-ITD mutation in acute myeloid leukemia VANFLYTA Package Information Strength Package NDC Code 17.7 mg 28‐count bottle 65597‑0504‑28 14‐count bottle 65597‑0504‑04 26.5 mg 28‐count bottle 65597‑0511‑28 14‐count bottle 65597‑0511‑04…

Read More
Previous
1 … 111213 … 17
Next

No alerts match your filters.

BuyandBill.com — Physician Administered Drug Pricing

HCPCS Level II codes and descriptors are approved and maintained jointly by the alpha-numeric editorial panel (consisting of CMS, America's Health Insurance Plans, and Blue Cross and Blue Shield Association).

CPT® codes and descriptions are copyright American Medical Association (AMA). All rights reserved

Review us on Trustpilot
  • Email us [email protected]

Tools & Lookups

  • Search
  • HCPCS Code Lookup
  • NDC Lookup
  • Drug Price Lookup
  • Billing Calculator
  • Drug Comparative Graphing
  • Biosimilar Analysis
  • Part B Reimbursement
  • All Drug Codes

Coding References

  • CPT Administration Codes
  • HCPCS Modifiers
  • HCPCS Approvals
  • Medically Unlikely Edits
  • Place of Service Codes
  • NDC Listing Errors
  • SAD Exclusion List
  • Wastage Guidance (JZ & JW)

Learn

  • Blog
  • Newsletter
  • Bobbi Buell's Newsletter
  • Glossary
  • Buy-and-Bill Basics
  • Biosimilars
  • 505(b)(2)
  • Drug Shortages

Solutions

  • Drug Sponsorship
  • Drug Market Research

Company

  • About B&B
  • Subscription Options
  • Contact Us
  • Schedule a Consultation
  • Sitemap

© 2026 BuyandBill.com, a product of Alchemy Healthcare Solutions LLC. All rights reserved

  • Privacy Policy
  • Terms of Service
BuyandBill.com Analytics

Chart a whole drug class in one screen.

The Comparative Report puts ASP, the Medicare payment limit, WAC and AWP for up to 15 drugs on one timeline. Ten-plus years of monthly history, per HCPCS unit.

  • Four benchmarks plus the ASP/WAC ratio on the same axis
  • Prebuilt biosimilar, therapeutic-area and mechanism groups
  • Index to 100 to compare a $7 drug against a $90 one
  • Sortable table, reference multiples, saved reports, PDF export
See it in action

Included with BuyandBill Pro for $37/month billed annually.

Trastuzumab class, seven products

7 of 7products fell
▼ 90.0%steepest decline
8.6×price spread
The Comparative Report showing seven trastuzumab products: ASP range $7.73 to $66.27, median $27.16, prices fell 7 of 7, and all seven ASP curves plotted from 2015 to 2026.

Actual published ASP, Jan 2015 to Aug 2026.